When the surface of the eye is injured or chronically inflamed, ordinary lubricating drops may not be enough. Amniotic membrane therapy for eyes is a specialized treatment that may help protect the cornea, reduce inflammation, and support healing when a patient has significant dry eye or ocular surface disease.
For the right patient, it can offer meaningful relief during a difficult flare. It is not a replacement for a complete dry eye plan, and it is not necessary for every case of irritation or redness. A thorough eye examination helps determine whether this treatment fits the underlying cause of a patient’s symptoms.
What is amniotic membrane therapy for eyes?
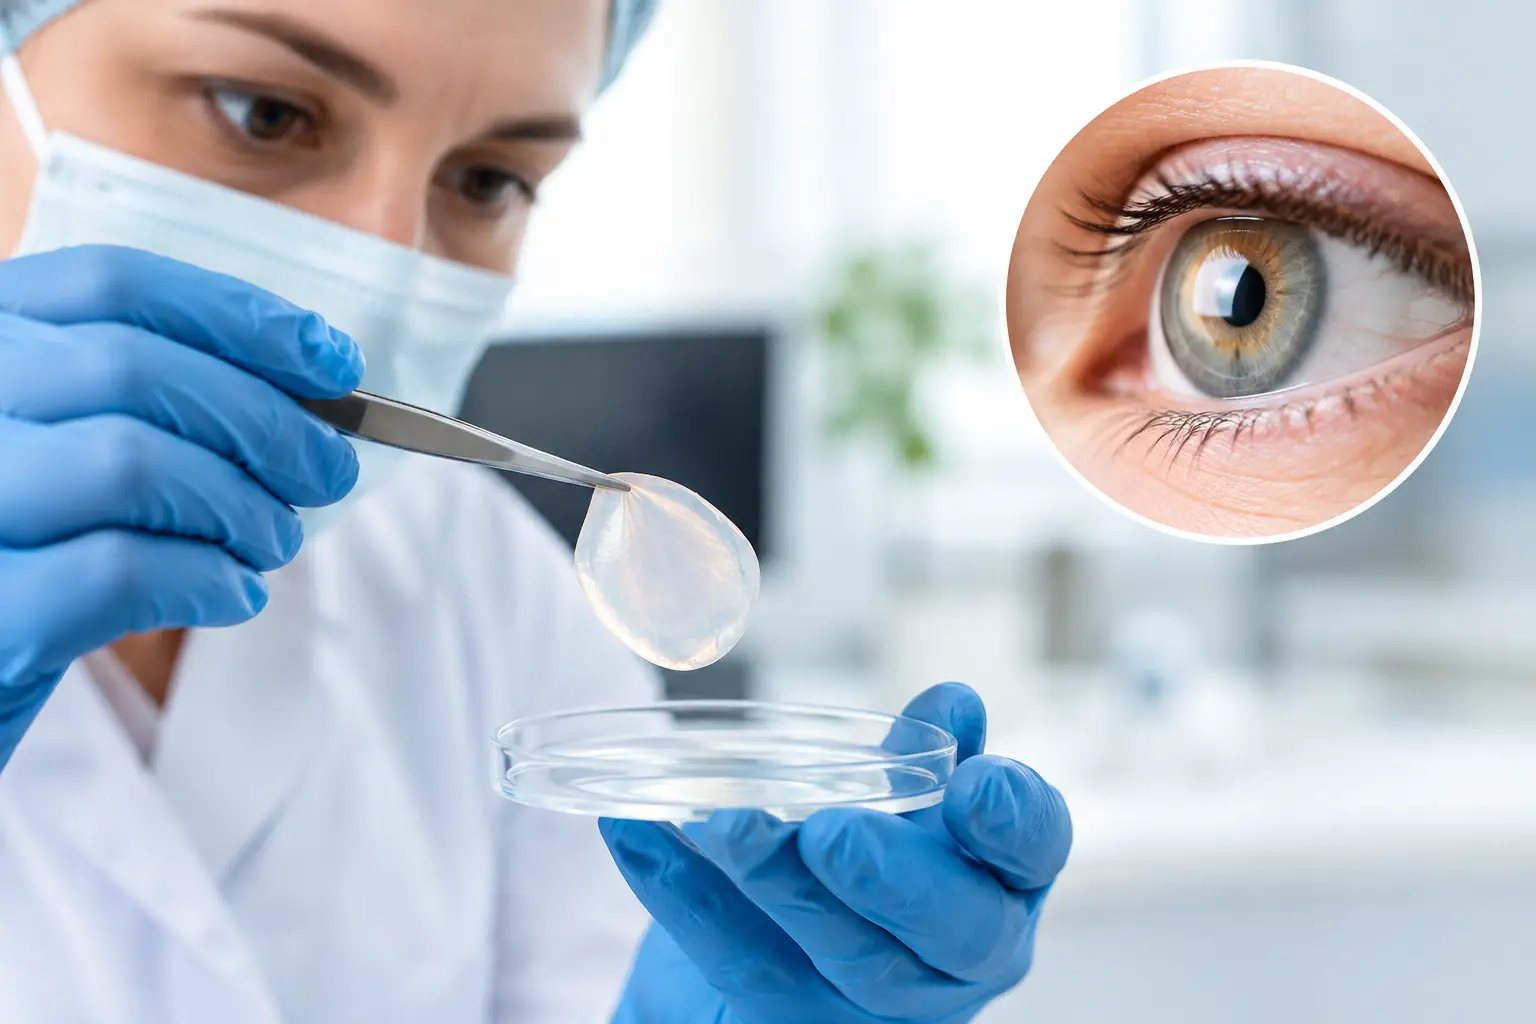
Amniotic membrane is a thin tissue obtained from the innermost layer of a donated placenta after a planned cesarean delivery. It is carefully screened, processed, and preserved for medical use. The tissue does not contain living cells from the donor in the form used for eye care, and it is designed to serve as a temporary protective covering for the ocular surface.
In eye care, the membrane is used because it contains naturally occurring components that may help calm inflammation, support the growth of healthy surface cells, and limit scarring. Think of it as a protective biologic bandage for the cornea and surrounding surface of the eye.
Depending on the product and the clinical need, the membrane may be placed under a soft bandage contact lens or mounted in a ring that rests on the eye. Some forms dissolve over time, while others are removed by the doctor after a period of healing.
When might this treatment be recommended?
Amniotic membrane therapy is generally considered when the cornea or ocular surface needs more support than artificial tears, prescription drops, warm compresses, or routine dry eye care can provide. It may be recommended for severe dry eye with surface damage, persistent corneal defects, recurrent corneal erosions, significant inflammation, chemical injury, or complications after eye surgery.
Patients with conditions such as neurotrophic keratitis, filamentary keratitis, exposure-related dryness, or certain autoimmune-related dry eye concerns may also be candidates. The decision is highly individual. Two people can describe the same burning or gritty sensation yet need very different care because the cause of their symptoms is different.
A comprehensive exam matters. Your eye doctor may assess the tear film, eyelid health, corneal staining, meibomian glands, vision, and the overall integrity of the eye’s surface. Advanced imaging and testing can help identify whether the concern is primarily dryness, inflammation, nerve-related corneal disease, allergy, infection, or another condition requiring a different approach.
It is not a first-line answer for every dry eye case
Many patients improve with a targeted treatment plan that may include preservative-free tears, lid hygiene, prescription medication, punctal plugs, specialty contact lenses, or in-office dry eye treatments such as IPL. Amniotic membrane therapy is typically reserved for cases in which the surface of the eye is more compromised or needs prompt healing support.
That distinction is helpful because it sets realistic expectations. This treatment can be very valuable, but it works best as part of a diagnosis-driven plan rather than as a one-size-fits-all solution for dry eye.
What happens during treatment?
Placement is performed in the office. Before treatment, numbing drops are usually used to improve comfort. The doctor then positions the membrane over the affected area of the eye, either with a ring-supported device or another appropriate method.
The process itself is generally quick. After placement, vision may be blurry, especially when a ring device is used. The eye may feel full, watery, or mildly irritated at first. These sensations are common because the eye is adjusting to the device and because the corneal surface may already be sensitive.
Patients are usually asked to return for follow-up so the doctor can monitor healing and determine when the membrane or supporting device should be removed. Treatment duration varies. Some patients wear the membrane for several days, while the appropriate timeline for others may be shorter or longer based on the condition being treated and the type of membrane used.
Your doctor may prescribe drops during the healing period and will explain whether to continue or pause your usual dry eye medications. Follow those instructions closely. Do not rub the eye or remove a device yourself unless your doctor has specifically told you to do so.
Benefits and realistic expectations
The central goal of amniotic membrane therapy is to give a damaged ocular surface a better environment for recovery. Patients may experience less pain, light sensitivity, redness, foreign-body sensation, and fluctuating vision as the surface heals. In some cases, the improvement can be noticeable within days.
Still, response varies. If dry eye is driven by long-term meibomian gland dysfunction, autoimmune disease, incomplete blinking, medication effects, or another ongoing issue, the membrane may help resolve an acute flare without eliminating the root cause. Continuing care is often needed to protect the gains made during treatment.
For example, a patient whose cornea has been damaged by severe evaporative dry eye may feel substantially better after treatment but still need ongoing lid care, tear support, and inflammation management. The practical value of the membrane is not that it permanently cures every source of dryness. It may help interrupt a cycle of inflammation and surface injury so longer-term treatment can work more effectively.
Risks, precautions, and when to call your eye doctor
Amniotic membrane products used in eye care are processed under strict standards, but no medical treatment is without potential risks. Temporary discomfort, blurred vision, tearing, device awareness, and redness can occur. A ring-supported device can be more noticeable than a standard contact lens.
Infection is uncommon but serious, particularly when the eye surface is already compromised. Contact your eye doctor promptly if you develop worsening pain, increasing redness, discharge, a sudden drop in vision, marked light sensitivity, or if the device shifts or falls out. Do not assume new symptoms are simply part of the healing process.
Your doctor will also determine whether active infection, certain eye conditions, or your medical history make another treatment more appropriate. Be sure to mention all eye drops, contact lens use, prior surgeries, allergies, and health conditions at your appointment.
Questions worth asking before treatment
A clear conversation can make treatment feel less intimidating. Ask what is causing the surface damage, what type of membrane is being recommended, how long it is expected to remain in place, and what your vision and comfort may be like during recovery. It is also reasonable to ask what follow-up care will be needed and whether insurance coverage may apply to your specific diagnosis and plan.
The answers should be specific to your eyes, not just the treatment in general. A patient-first practice will explain the expected benefits, limitations, alternatives, and costs before moving forward.
At Mountain Eye Care, dry eye treatment begins with understanding what is affecting the eye’s surface and building care around the patient’s symptoms, findings, and daily needs. If persistent dryness, pain, redness, or light sensitivity is affecting your comfort or vision, an eye health evaluation can help clarify whether amniotic membrane therapy or another targeted option is appropriate.
Healing the eye’s surface often takes more than reaching for another bottle of drops. The right diagnosis and timely care can help protect both day-to-day comfort and long-term vision.